Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 11—November 2026
Dispatch
Post–COVID-19 Expansion of Streptococcus pyogenes Lineages Causing Toxic Shock Syndrome, Japan, 2023–2024
 , Hitoshi Otsuka, Mari Sasaki, Takahiro Yamaguchi, Yoshimi Date, Yu Kazawa, Kazuki Saito, Kaho Ikeda, Rumi Okuno, Yukihiro Akeda, and The Working Group for Beta-Hemolytic Streptococci in Japan1
Suggested citation for this article
Abstract
We analyzed 919 Streptococcus pyogenes isolates from laboratory-confirmed streptococcal toxic shock syndrome cases in Japan during 2023–2024. Post–COVID-19 resurgence was driven by expansion of M1UK (49.8%) and emerging M113SNPs (37.4%) lineages, replacing ancestral M1global. M113SNPs were associated with younger patient age and higher death rates in unadjusted analyses.
Streptococcal toxic shock syndrome (STSS) is a rapidly progressive, life-threatening invasive disease primarily caused by group A Streptococcus (Streptococcus pyogenes) bacteria (1,2). After relaxation of nonpharmaceutical interventions for COVID-19 in Japan, resurgence in STSS was observed, coinciding with reports of M1UK lineage expansion (3). We conducted a nationwide molecular epidemiologic study to clarify the contribution of emm1 sublineages to this increase.
This laboratory-based study analyzed S. pyogenes isolates from laboratory-confirmed STSS cases reported across Japan during January 1, 2023–December 31, 2024. STSS is notifiable under Infectious Disease Control Law; surveillance is coordinated by the National Institute of Infectious Diseases (NIID; Tokyo, Japan) with prefectural public health institutes and sentinel hospitals. We applied US Centers for Disease Control and Prevention criteria: isolation of group A Streptococcus from a normally sterile site plus clinical shock with multiorgan involvement (4).
A total of 919 isolates were collected from 1,477 reported STSS cases, 186 isolates in 2023 and 733 in 2024. Coverage was 62.2% overall, 45.9% in 2023, and 68.4% in 2024. Specimens from routine care were submitted to 7 regional reference laboratories (Fukushima, Tokyo, Kanagawa, Toyama, Osaka, Yamaguchi, and Oita) and NIID. Species identification was performed using API 20 Strep (bioMérieux, https://www.biomerieux.com), and Lancefield group determination used latex agglutination kits (Iwaki Corporation, https://www.iwaki-kk.co.jp). The NIID Ethics Review Board approved this public health surveillance under Article 15 of the Infectious Disease Law; individual consent was waived.
We performed emm genotyping by PCR and sequencing of the 5′ region using primers emm-1/emm-2 and sequencing primer emmseq2 with 180-bp sequences matched to the CDC emm database (5). We assessed speA and speC genes by primers described previously (6). Among the emm1 isolates, we identified M1UK, M123SNPs, M113SNPs, and M1global lineages using allele-specific PCR targeting single-nucleotide polymorphisms (SNPs) in rofA, gldA, and pstB (7).
To investigate the differences between the M1UK strain and the M113SNPs strain, we amplified the upstream region of the speA gene using the M1UK forward (cctagtctatacagccaaaaagc) primer and the M1UK reverse (gcattgatggagctggtggg) primer and sequenced them using the M1UKseq1 (tatacagccaaaaagcgagg) primer. We confirmed that mutations observed in the M1UK strain were not present in all the strains obtained as M113SNPs, which was consistent with the results of allele-specific PCR targeting SNPs in rofA, gldA, and ptsB. We conducted statistical analyses in Ekuseru-Toukei version 4.10 (Social Survey Research Information Co., Ltd, https://bellcurve.jp) using t test for age and Fisher exact test for deaths; we considered p<0.05 significant.
Figure 1

Figure 1. Isolates of emm gene types by month in study of post–COVID-19 expansion of Streptococcus pyogeneslineages causing toxic shock syndrome, Japan, 2023–2024. y-axis indicates the number of...
Among 919 STSS isolates, we identified 31 emm types, including 2 untypeable strains with signal sequence deletions (Appendix Table 1, https://wwwnc.cdc.gov/EID/article/32/11/26-0336-App1.pdf). Type emm1 predominated (470/919, 51.1%), followed by emm12 (12.3%), emm89 (11.5%), emm49 (7.9%), and emm81 (5.8%), accounting for >85% of isolates overall (Appendix Figure 1, panel A). After adjusting for collection rates (Appendix Table 2), emm1 increased markedly in 2024 (Appendix Figure 1, panel B). National surveillance data showed emm1-associated STSS declined during 2020–2022 but rose after mask policy relaxation (March 13, 2023), reaching 60–80 cases/month during January–June 2024 (8,9). Most other types (emm89, emm81, emm49) remained stable, whereas emm12 also increased (Figure 1).
Figure 2
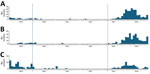
Figure 2. Isolates of M1 lineages by month in study of post–COVID-19 expansion of Streptococcus pyogeneslineages causing toxic shock syndrome, Japan, 2023–2024. y-axis indicates the number of calculated 100% isolates...
Among 470 emm1 isolates, we identified M1UK (234 [49.8%]), M113SNPs (176 [37.4%]), and M1global (60 [12.8%]) lineages. Compared with 2019 (M1global >60%; M1UK 24%; M113SNPs 12%), 2023–2024 showed replacement: M1UK increased from 44% to 51% and M113SNPs from 29% to 39%, but M1global decreased from 26% to 11% (Appendix Figure 2). Each lineage rose after mask relaxation (Figure 2).
Among the 470 emm1 isolates, 458 (97.4%) were speA positive: 283 (60.2%) speA-only, 175 (37.2%) both speA and speC, and 8 (1.7%), speC-only. Four (0.9 %) were positive but for neither speA nor speC. M1UK mainly carried speA-only (202 [86.3%]), M113SNPs harbored both genes (143 [81.3%]), and M1global was predominantly speA-only (55 [90.2%]) (Appendix Table 3).
M113SNPs infections occurred in younger patients (average age 58.3 years; interquartile range [IQR] 43–75 years) and were associated with higher risk for death (mortality rate 31.3%) than non-emm1 cases isolated during the same period, in which the average age was 62.7 (IQR 50–78) years and mortality rate 23.2%. M1UK also affected younger patients (average age 54.9 [IQR 41–69] years) but showed comparable mortality rate (20.5%), whereas M1global showed no significant differences in either age (average age 58.9 [IQR 46–72] years) or mortality rate (20.0%) (Table 1).
M113SNPs infections are associated with younger patients and higher mortality rate. Because age is a major determinant of STSS outcomes, we assessed the association between age and mortality to confirm that the observed differences in mortality were not influenced by age. Although we observed no significant differences in sex or age distribution between cases of STSS caused by M113SNPs and those caused non-emm1 strains (Table 2), mortality was significantly higher in patients with M113SNPs infections (31.3% vs. 23.2%; odds ratio [OR] 1.51 [95% CI 1.02–2.22]). Age-stratified analysis further revealed significantly higher mortality in the M113SNPs group among patients 25–39 years of age (OR 5.00 [95% CI 1.29–19.3]) and 70–84 years of age (OR 2.24 [95% CI 1.14–4.41]).
Nationwide surveillance links Japan’s post–COVID-19 STSS resurgence to expansion of emm1 S. pyogenes, driven by replacement of M1global with M1UK and M113SNPs lineages. That pattern parallels M1UK increases reported in Europe (9,10) and highlights the emergence of M113SNPs, which was associated with higher mortality than were non-emm1 strains, as well as diversity in speA/speC profiles and a younger age distribution.
The temporal association with relaxation of nonpharmaceutical interventions suggests increased opportunities for transmission in school and community settings. Clinical heterogeneity observed among emm1 sublineages underscores the value of lineage-level molecular surveillance for risk assessment.
Limitations of our study included 62% coverage of reported cases, restriction to STSS cases, limited study periods, and incomplete clinical data use that required us to perform unadjusted analyses. Although infection with M113SNPs was associated with higher mortality, that finding should be interpreted cautiously because it might be affected by unmeasured confounding factors such as underlying conditions, treatment differences, or disease severity. Our results should therefore be considered exploratory and do not establish an independent effect of the M113SNPs lineage on clinical outcomes.
Nonetheless, application of standardized national methods to 919 isolates provided evidence of rapid lineage replacement. We recommend continued molecular surveillance needed to monitor M1UK and M113SNPs globally, identify emerging variants, and inform public health responses to future S. pyogenes epidemics.
Dr. Ikebe is a microbiologist at the National Institute of Infectious Diseases in Tokyo, Japan. His research interests include the microbiology of β-hemolytic streptococci.
Acknowledgments
Other members of the Working Group for Beta-Hemolytic Streptococci in Japan: Rin Satoh, Yui Kawabata (Hokkaido Institute of Public Health); Yusei Sekiya (Akita Prefectural Research Center for Public Health and Environment); Takuya Yamanaka (Iwate Prefectural Research Institute for Environmental Sciences and Public Health); Mayu Suzuki (Yamagata Prefectural Institute of Public Health); Satoko Yamaya (Miyagi Prefectural Institute of Public Health and Environment); Naomi Kogure (Niigata Prefectural Institute of Public Health and Environmental Sciences); Ryoya Akiyama (Niigata City Institute of Public Health and Environment); Yumi Uchitani (Tokyo Metropolitan Institute of Public Health); Yumi Tamura (Sagamihara City Institute of Public Health); Kentaro Tomari (Saitama City Institute of Health Science and Research); Daichi Sakamoto (Saitama Prefectural Institute of Public Health); Yoshiho Takahashi (Shizuoka City Institute of Environmental Sciences and Public Health); Takahiro Shimoda (Gunma Prefectural Institute of Public Health and Environmental Sciences); Akira Wakatsuki (Utsunomiya City Institute of Public Health and Environment); Asami Sekikawa (Tochigi Prefectural Institute of Public Health and Environmental Science); Akio Nagano (Chiba City Institute of Health and Environment); Emiri Nishizato, Yusuke Yodotani (Kawasaki City Institute for Public Health); Natsuko Kawabata, Yuko Matsumoto, Takako Katakura (Yokosuka City Institute of Public Health); Takako Nakayama, Mitsuru Kishizawa (Chiba Prefectural Institute of Public Health); Yurie Uchiyama (Nagano Environmental Conservation Research Institute); Marino Oichi (Mie Prefecture Health and Environment Research Institute); Sachiko Nakamura (Ishikawa Prefectural Institute of Public Health and Environmental Science); Mio Nishide (Kanazawa City Environmental Sanitation Testing Center); Noriko Saito (Aichi Prefectural Institute of Public Health); Koji Yokoyama, Shiho Tajima (Fukui Prefectural Institute of Public Health and Environmental Science); Tomohiro Yamaguchi (Gifu Prefectural Research Institute for Health and Environmental Sciences); Chiho Furuta (Gifu Municipal Institute of Public Health); Masaki Anraku (Osaka Institute of Public Health); Shinya Okita, Hidenobu Shimizu (Kyoto City Institute of Health and Environmental Sciences); Kenji Konaka, Yoshiyuki Kawahara (Kyoto Prefectural Institute of Public Health and Environment); Naoaki Iwasaki (Sakai City Institute of Public Health); Mayako Koide (Shiga Prefectural Institute of Public Health); Noriko Nakanishi, Shoko Komatsu (Kobe Institute of Health); Miyuki Saeki, Yui Tsukiyama (Nara Prefecture Institute of Health); Kento Tarao, Shoko Hirata (Amagasaki City Institute of Public Health); Haruka Takeshita (Himeji City Institute of Environment and Health); Maho Ikebata (Hyogo Prefectural Institute of Public Health Science); Akira Kuwata (Wakayama Prefectural Research Center of Environment and Public Health); Takakiyo Ikebata (Wakayama City Institute of Public Health); Momoho Onda (Tottori Prefectural Institute of Public Health and Environmental Science); Jun Kawase, Yuta Kawakami (Shimane Prefectural Institute of Public Health and Environmental Science); Hisahiro Kawai (Okayama Prefectural Institute for Environmental Science and Public Health); Takahiro Hiratsuka, Keiko Ishii (Hiroshima Prefectural Technology Research Institute, Public Health and Environment Center); Hiromi Tsukiji (Hiroshima City Institute of Public Health); Chizuko Kimura, Shintarou Hirai (Ehime Prefectural Institute of Public Health and Environmental Science); Atsuko Kageyama, Masami Uchida (Kochi Prefectural Public Health and Environmental Science Research Institute); Chiharu Katamune (Fukuoka Institute of Health and Environmental Sciences); Yuri Abe (Fukuoka City Institute of Health and Environment); Etsuko Nakamura (Kitakyushu City Institute of Health and Environmental Sciences); Yumiko Amari (Saga Prefectural Institute of Public Health and Pharmaceutical Research); Yuji Migita (Nagasaki Prefectural Institute of Environment and Public Health); Emi Ogawa (Miyazaki Prefectural Institute for Public Health and Environment); Tsuyoshi Kudeken (Okinawa Prefectural Institute of Health and Environment). Aomori Prefectural Institute of Health, Sendai City Public Health Institute, Kagawa Prefectural Research Institute for Environmental Science and Public Health, and Tokushima Prefectural Public Health Pharmaceutical and Environmental Sciences Center are also represented in the Working Group.
This work was supported by the Ministry of Health, Labour and Welfare of Japan (grant no. 25HA2001).
References
- Brouwer S, Rivera-Hernandez T, Curren BF, Harbison-Price N, De Oliveira DMP, Jespersen MG, et al. Pathogenesis, epidemiology and control of group A Streptococcus infection. Nat Rev Microbiol. 2023;21:431–47. DOIPubMedGoogle Scholar
- Stevens DL, Bryant AE. Severe group A streptococcal infections. In: Ferretti JJ, Stevens DL, Fischetti VA, eds. Streptococcus pyogenes: basic biology to clinical manifestations. 2nd ed. Oklahoma City (OK): University of Oklahoma Health Sciences Center; 2022. p. 583–604.
- Japan Institute for Health Security, National Institute of Infectious Diseases. Risk assessment for streptococcal toxic shock syndrome (STSS) in Japan. 2024 [cited 2026 Feb 12]. https://id-info.jihs.go.jp/en/risk-assessment/streptococcal-toxic-shock-syndrome/240701_NIID_STSS_2_Eng.pdf
- Centers for Disease Control and Prevention. Case definition: streptococcal toxic shock syndrome [cited 2026 Feb 12]. https://www.cdc.gov/group-a-strep/hcp/clinical-guidance/streptococcal-toxic-shock-syndrome.html
- Beall B, Facklam R, Thompson T. Sequencing emm-specific PCR products for routine and accurate typing of group A streptococci. J Clin Microbiol. 1996;34:953–8. DOIPubMedGoogle Scholar
- Ikebe T, Murayama S, Saitoh K, Yamai S, Suzuki R, Isobe J, et al.; Working Group for Streptococci in Japan. Surveillance of severe invasive group-G streptococcal infections and molecular typing of the isolates in Japan. Epidemiol Infect. 2004;132:145–9. DOIPubMedGoogle Scholar
- Zhi X, Li HK, Li H, Loboda Z, Charles S, Vieira A, et al. Emerging invasive group A Streptococcus M1UK lineage detected by allele-specific PCR, England, 2020. Emerg Infect Dis. 2023;29:1007–10. DOIPubMedGoogle Scholar
- Ikebe T, Okuno R, Uchitani Y, Yamaguchi T, Isobe J, Maenishi E, et al.; Working Group for Beta-Hemolytic Streptococci in Japan. Epidemiological shifts in and impact of COVID-19 on streptococcal toxic shock syndrome in Japan: a genotypic analysis of group A Streptococcus isolates. Int J Infect Dis. 2024;142:
106954 . DOIPubMedGoogle Scholar - Vieira A, Wan Y, Ryan Y, Li HK, Guy RL, Papangeli M, et al. Rapid expansion and international spread of M1UK in the post-pandemic UK upsurge of Streptococcus pyogenes. Nat Commun. 2024;15:3916. DOIPubMedGoogle Scholar
- Vesty A, Ren X, Sharma P, Lorenz N, Proft T, Hardaker A, et al. The emergence and impact of the M1UK lineage on invasive group A Streptococcus disease in Aotearoa New Zealand. Open Forum Infect Dis. 2024;11:
ofae457 . DOIPubMedGoogle Scholar
Figures
Tables
Suggested citation for this article: Ikebe T, Otsuka H, Sasaki M, Yamaguchi T, Date Y, Kazawa Y, et al. Post–COVID-19 expansion of Streptococcus pyogenes lineages causing toxic shock syndrome, Japan, 2023–2024. Emerg Infect Dis. 2026 Nov [date cited]. https://doi.org/10.3201/eid3211.260336
Original Publication Date: October 16, 2026
1Additional members of this group who contributed data are listed at the end of this article.
Table of Contents – Volume 32, Number 11—November 2026
| EID Search Options |
|---|
 Advanced Article Search – Search articles by author and/or keyword. |
 Articles by Country Search – Search articles by the topic country. |
 Article Type Search – Search articles by article type and issue. |
Please use the form below to submit correspondence to the authors or contact them at the following address:
Tadayoshi Ikebe, Department of Bacteriology I, National Institute of Infectious Diseases, Japan Institute for Health Security, 1-23-1 Toyama, Shinjuku-ku, Tokyo 162-8640, Japan
Top