Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 11—November 2026
Synopsis
Subacute Sclerosing Panencephalitis after Measles Outbreaks, the Philippines, 2007–2022
 , Maridel S. Ramones, and Roland Dominic G. Jamora
Suggested citation for this article
Abstract
Subacute sclerosing panencephalitis (SSPE) is a delayed, almost uniformly fatal complication of measles. The Philippines had measles outbreaks in 2010–2011, 2013, and 2018–2019; the last was the largest in the World Health Organization Western Pacific Region. Published SSPE data from the Philippines end in 2015. We reviewed all 20 children admitted with SSPE to a tertiary pediatric hospital in Quezon City during 2007–2022 and estimated year of measles infection. Median patient age was 6.2 years at hospital admission and 0.7 years at reported measles illness. Five (25.0%) of 20 admissions occurred in 2022, and estimated infection dates placed 4 patients within the 2018–2019 outbreak; all were admitted during 2020–2022. Given the multiyear latency of SSPE, additional cases might emerge over coming years. Reported measles history could not be established in one quarter of patients. Strengthened measles surveillance and sustained 2-dose vaccination coverage are needed.
Subacute sclerosing panencephalitis (SSPE) is a progressive neurodegenerative disorder caused by persistent central nervous system infection with a defective, hypermutant measles virus. It typically follows measles acquired in early childhood after a latency of years and is almost always fatal (1,2). Because SSPE follows measles by years rather than weeks, the neurologic consequences of an outbreak do not become visible until long after the outbreak has ended.
Measles vaccination was introduced in the Philippines in 1983; the first routine dose is scheduled at 9 months of age (3). Nationwide immunization campaigns in 1998 and 2004 were followed by historically low measles incidence in 2006 (3). First-dose measles-containing vaccine coverage later declined from 92% in 2004–2007 to 80% in 2015–2016 and 64% in 2021 (4). Reported measles cases rose sharply during a 2018–2019 outbreak, from 2,428 in 2017 to 48,525 in 2019, the largest outbreak in the World Health Organization Western Pacific Region during that period (5).
Published data on SSPE in the Philippines are limited; the largest local series described children seen at a single tertiary hospital during 2005–2015 (6). No published series from the Philippines spans the period during which children infected in the 2018–2019 outbreak would be expected to demonstrate symptoms of SSPE. We describe children admitted with SSPE to a tertiary government pediatric hospital over 16 years and examine the distribution of their estimated years of measles infection against the national outbreak record.
Design and Setting
We retrospectively reviewed the records of all children admitted to National Children’s Hospital, a tertiary government pediatric hospital in Quezon City, the Philippines, with a final diagnosis of SSPE during January 1, 2007–December 31, 2022. All such patients were enumerated. The 2007 start date reflects the period from which complete institutional records and corresponding registry data were available.
Case Definition
We modified the case definition from Dyken’s criteria (1). We defined a case as a clinical diagnosis of SSPE by the attending pediatric neurologist on the basis of progressive neurologic deterioration with qualitatively positive measles antibody in cerebrospinal fluid (CSF), serum, or both. We excluded children with bacterial, tuberculous, or viral meningitis and children with intracranial masses. Because quantitative measles antibody titers, CSF globulin fractionation, brain biopsy, and uniform electroencephalography were unavailable, we could not apply the full Dyken criteria; we classified cases as clinically diagnosed SSPE with varying levels of supportive evidence.
Variables
Age at reported measles infection and reported measles history came from parental or guardian recall recorded at admission; measles history was recorded as reported, absent, or unknown. Vaccination status was likewise based on parent or guardian report recorded at admission and was not consistently verified against immunization records.
Estimation of Year of Reported Measles Infection
For each patient, we calculated the interval between measles infection and development of SSPE as age at hospital admission minus age at measles infection. We obtained the estimated calendar year of measles infection by subtracting that interval from the year of admission. We then compared estimated infection years with the recorded periods of national measles outbreak activity.
For the 14 children with a parent- or guardian-reported history of measles, we calculated the interval between reported measles illness and hospital admission. We excluded 3 children with a reported measles-to-admission interval of <1 year from the interval analysis, because such a short interval is atypical for SSPE and the timing of the reported measles illness could not be independently verified. A very short interval can also reflect acute measles encephalitis (within 14 days of rash onset) or acute disseminated encephalomyelitis (within weeks), rather than SSPE, which follows a latency of years (1).
Statistical Analysis
We summarized categorical variables as frequencies and percentages and summarized continuous variables as medians with interquartile ranges. We did not group patients by admission year for comparison, because the multiyear interval between infection and admission makes such grouping uninterpretable. Analyses used Stata 16.1 (StataCorps LLC, https://www.stata.com) and Microsoft Excel (https://www.microsoft.com). The protocol was approved by the National Children’s Hospital Institutional Review Board (approval no. NCH-IRB 2023–12-NCT) using unlinked, deidentified data.
Figure
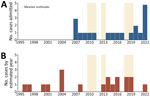
Figure. Hospital admissions for subacute sclerosing panencephalitis (SSPE) in study of SSPE after measles outbreaks, Philippines, 2007–2022. A) SSPE admissions by year (blue); B) the same cases by estimated year of...
Twenty children admitted during January 1, 2007–December 31, 2022, met the case definition. Cases were unevenly distributed across the study period (Figure, panel A). Eight (40.0%) of the 20 admissions occurred in the final 3 years of the series, and 5 (25.0%) admissions occurred in 2022 alone.
Four patients had an estimated measles infection year of 2018 or 2019, corresponding to the national outbreak period (Figure, panel B); all 4 had a reported measles history and positive CSF antibody, and all were admitted during 2020–2022 with intervals of 2.1–3.5 years since measles infection. For 3 patients, the estimated infection year was 2004; estimated infection year for 1 patient was 2013. Most patients with an estimable year (14 of 19) were infected outside recognized outbreak periods, consistent with continued transmission between outbreaks.
SSPE was suspected at time of admission in 9 (45.0%) patients. The remainder were admitted under other working diagnoses: probable intracranial mass in 4 (20.0%) patients, meningitis in 3 (15.0%) patients, encephalitis in 2 (10.0%) patients, and 1 (5.0%) each of acute rheumatic fever and traumatic brain injury. At discharge, 18 (90.0%) patients carried a diagnosis of SSPE and 2 (10.0%) patients probable SSPE.
Of the 20 patients, 14 (70.0%) patients were male and 6 (30.0%) were female. The median age was 6.2 years at admission and 0.7 years at reported measles illness; 10 of the 19 patients with an estimable age were infected before the age of 9 months. Eight children had stunting or wasting, and 3 had comorbidities. A reported measles history was present in 15 (75.0%), unknown in 4 (20.0%), and absent in 1 (5.0%). Seventeen (85.0%) patients had received >1 measles-containing vaccine; 11 (55.0%) patients had received a single dose only. Twelve (60.0%) patients were admitted in stage 2 and 5 (25.0%) were admitted in stage 3 (Table; Appendix Table). Among the 14 children with a reported measles history, the median interval from measles to hospital admission was 5.8 (interquartile range 3.5–8.9) years.
Among the 20 children, 5 had progressive neurologic deterioration, tested positive for measles antibody in CSF, and had characteristic electroencephalography; 12 had progressive deterioration and antibody-positive CSF without electroencephalography; and 3 had progressive deterioration with antibody-positive serum only. Measles antibody testing of CSF was performed in 17 patients and was positive in all 17; serum antibody was tested in 13 and positive in all 13. Both were tested in 10 patients; 3 patients had serum testing alone. Electroencephalography was performed in 5 patients (25.0%); all showed patterns consistent with SSPE (7).
In this 16-year series, cases of SSPE clustered in recent years: 40% of admissions occurred in the last 3 years of the study period (2020–2022) and one quarter occurred in 2022 alone; 4 children had an estimated measles infection during the 2018–2019 outbreak. Because SSPE follows measles after a latency of years, those observations most likely represent the leading edge of a postoutbreak wave; additional cases might emerge over the coming years. For public health, the priority is heightened measles surveillance, early recognition of SSPE in children infected during recent outbreaks, and restoration of high 2-dose vaccination coverage.
The short intervals between measles infection and SSPE (2.1–3.5 years) seen in the 4 outbreak-associated cases do not indicate shortening latency: a child infected in 2018 cannot show an interval beyond 4 years in a series closing in 2022, so recent cases are truncated by the observation window. First-dose coverage fell to 64% by 2021, enlarging the susceptible pool beyond the 2018–2019 cohort. A comparable postoutbreak resurgence of SSPE has been reported from the United Kingdom (8).
A reported measles history was absent or unknown in a quarter of children; in those children, diagnosis rested on progressive neurodegeneration and presence of measles antibody in CSF or serum. Absence of a reported measles history is often used to argue against SSPE, yet such reasoning would have delayed or missed diagnosis in 5 of those 20 children. Measles antibody testing of CSF is therefore warranted in any child with progressive neurodegeneration and myoclonus, regardless of reported history.
Although 85% of children had received a measles-containing vaccine, that does not implicate vaccination: SSPE follows wild-type measles, not the vaccine (1,2). Ten of 19 patients were infected before 9 months, the age of the first scheduled measles-containing vaccine dose in the Philippines (3) and an age group at particularly high risk for SSPE (1,2), and most had received only 1 dose. Those findings support earlier and more complete 2-dose coverage and supplementary immunization during outbreaks.
The profile (male predominance, diagnostic delay of weeks to months) was broadly comparable with an earlier Philippines series (6); undernutrition and social disadvantage, noted locally (9), might limit timely vaccination and thereby raise measles and SSPE risk. SSPE cases in the Philippines currently cannot be staged against international criteria because quantitative antibody titers, CSF globulin fractionation, and consistent electroencephalography and neuroimaging are unavailable, a diagnostic-capacity gap worth closing in a country with recurrent measles outbreaks.
The first limitation of this study is that, as a single-center retrospective review of 20 patients, it might not represent SSPE nationally, and no population denominator was available, so counts cannot be expressed as rates. Second, measles history, age at infection, and vaccination status were based on guardian recall and could not be verified; the infection-to-SSPE interval is therefore estimated and could not be determined in one quarter of children. Measles antibody was reported only qualitatively, and 3 children were diagnosed using serum antibody without CSF confirmation, although the temporal findings were unchanged when restricted to the 17 with CSF confirmation. Finally, molecular confirmation and genotyping, which require tissue, were not performed, and outcome after discharge was not available.
In conclusion, measles antibody testing of CSF should be considered in any child with progressive neurodegeneration and myoclonus, irrespective of the reported measles history. Additional SSPE cases temporally associated with the 2018–2019 outbreak might continue to occur over the remainder of the 2020s. National surveillance for SSPE should be strengthened accordingly. Laboratory capacity should be developed for quantitative measles antibody titration in serum and CSF and for CSF globulin fractionation, so that Philippine cases can be characterized against international diagnostic criteria. Prospective studies capturing outcome and survival in children from the Philippines with SSPE are needed, as is evaluation of supportive and disease-modifying treatment in this population, building on the limited local experience with intravenous immunoglobulin (10). Efforts to restore and sustain 2-dose measles vaccination coverage, including supplementary immunization activities during outbreaks, remain the only means of preventing disease. Where postmortem or biopsy tissue is available, molecular confirmation of measles RNA and genotyping to link cases to circulating strains would strengthen future SSPE surveillance.
Dr. Palisoc is a pediatric neurologist in the Section of Pediatric Neurology, National Children’s Hospital, Quezon City, and Associate Professor II at the Neuroscience Department, College of Medicine, San Beda University, Manila. Her research interests include pediatric epilepsy, neuroinfectious disease, and medical education.
Acknowledgments
We thank Tereynz Paul D. Mendoza for statistical analysis.
M.P.P. conceived the study, designed and performed the analysis, and drafted the manuscript. M.S.R. acquired the data and verified the references and source data. R.D.G.J. reviewed the manuscript critically for important intellectual content. All authors approved the final version and agree to be accountable for all aspects of the work.
The authors used Claude (Anthropic, https://www.anthropic.com) in preparing this manuscript. The tool assisted with verification of statistical calculations from data extracted by the authors, generation of the figure, and drafting and revision of the manuscript text. All source data were collected by the authors. All analyses were checked against the source data, all references were verified by the authors against the statements they support, and all content was reviewed and approved by the authors, who take full responsibility for the accuracy and integrity of the work.
References
- Garg RK, Mahadevan A, Malhotra HS, Rizvi I, Kumar N, Uniyal R. Subacute sclerosing panencephalitis. Rev Med Virol. 2019;29:
e2058 . DOIPubMedGoogle Scholar - Jafri SK, Kumar R, Ibrahim SH. Subacute sclerosing panencephalitis—current perspectives. Pediatric Health Med Ther. 2018;9:67–71. DOIPubMedGoogle Scholar
- Takashima Y, Schluter WW, Mariano KM, Diorditsa S, de Quiroz Castro M, Ou AC, et al.; Centers for Disease Control and Prevention (CDC). Progress toward measles elimination—Philippines, 1998–2014. MMWR Morb Mortal Wkly Rep. 2015;64:357–62.PubMedGoogle Scholar
- World Health Organization. UNICEF. WHO/UNICEF estimates of national immunization coverage: Philippines, 2025 revision [cited 2026 Jul 23]. https://worldhealthorg.shinyapps.io/wuenic-trends
- Domai FM, Agrupis KA, Han SM, Sayo AR, Ramirez JS, Nepomuceno R, et al. Measles outbreak in the Philippines: epidemiological and clinical characteristics of hospitalized children, 2016–2019. Lancet Reg Health West Pac. 2022;19:
100334 . DOIPubMedGoogle Scholar - Rabanes AC, Cruz-Urbi CM. Demographic, clinical, imaging, and EEG characteristics of subacute sclerosing panencephalitis. Eur J Paediatr Neurol. 2017;21(Suppl 1).
- Ali S, Kumar H, Ullah S, Haq MAU, Gul NG, Kumar J. Electroencephalography patterns of subacute sclerosing panencephalitis. Cureus. 2021;13:
e15728 .PubMedGoogle Scholar - Lam T, Ranjan R, Newark K, Surana S, Bhangu N, Lazenbury A, et al. A recent surge of fulminant and early onset subacute sclerosing panencephalitis (SSPE) in the United Kingdom: an emergence in a time of measles. Eur J Paediatr Neurol. 2021;34:43–9. DOIPubMedGoogle Scholar
- Pipo-Deveza JR, Kusuhara K, Silao CLT, Lukban MB, Salonga AM, Sanchez BC, et al. Analysis of MxA, IL-4, and IRF-1 genes in Filipino patients with subacute sclerosing panencephalitis. Neuropediatrics. 2006;37:222–8. DOIPubMedGoogle Scholar
- Lukban MB, Chua-Macrohon BC, Salonga AM. The use of intravenous immunoglobulin in subacute sclerosing panencephalitis: a retrospective cohort study. Acta Med Philipp. 2013;47:46–50. DOIGoogle Scholar
Figures
Table
Suggested citation for this article: Palisoc MP, Ramones MS, Jamora RDG. Subacute sclerosing panencephalitis after measles outbreaks, the Philippines, 2007–2022. Emerg Infect Dis. 2026 Nov [date cited]. https://doi.org/10.3201/eid3211.261395
Original Publication Date: October 13, 2026
Table of Contents – Volume 32, Number 11—November 2026
| EID Search Options |
|---|
 Advanced Article Search – Search articles by author and/or keyword. |
 Articles by Country Search – Search articles by the topic country. |
 Article Type Search – Search articles by article type and issue. |
Please use the form below to submit correspondence to the authors or contact them at the following address:
Maela P. Palisoc, Neuroscience Department, College of Medicine, San Beda University, 638 Mendiola St, San Miguel, Manila 1005, Philippines
Top