Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 11—November 2026
Dispatch
Dirofilaria asiatica Infection and Asymptomatic Microfilaremia, Sri Lanka, 2025

Suggested citation for this article
Abstract
We report 2 cases of asymptomatic Dirofilaria microfilaremia in humans in Sri Lanka, detected during night blood surveillance for lymphatic filariasis in 2025. Partial sequence of microfilarial cytochrome c oxidase 1 gene revealed that both infections were caused by the novel species D. asiatica, originally described in Hong Kong as Candidatus D. honkongensis.
Dirofilariasis is an emerging mosquitoborne zoonosis caused by nematodes of the family Onchocercidae, genus Dirofilaria (1). Two main species are of relevance in veterinary and clinical practice, Dirofilaria immitis (dog heartworm) and D. repens. D. immitis worms have a wider distribution (Americas, Africa, Europe, and Australasia) and cause potentially life-threatening cardiopulmonary dirofilariasis in canids and felids and pulmonary lesions in accidental human infections. D. repens worms are limited to the Old World and cause subcutaneous and ocular dirofilariasis in canines, felines, and in accidental human infections.
A novel D. asiatica nematode species (formerly Candidatus Dirofilaria honkongensis) of canine origin was reported in Hong Kong in 2012 and subsequently in other countries in the region; it is gaining prominence as a zoonosis with diverse manifestations including cervical lymphadenopathy, abdominal subcutaneous masses, and subconjunctival nodules (2). Stray dogs and putative vector mosquitoes of genera Aedes, Culex, Mansonia, and Armigeres are abundant in Sri Lanka. Surveys in Sri Lanka have documented the presence of D. asiatica worms among 27.9% of canines with isolation of adult D. asiatica worms in subcutaneous nodules, scrota, and spermatic cords (3).
Adult filarial worms and their larval stages were historically identified on the basis of morphology and morphometry (4,5). However, differentiation of taxa was challenging because of morphologic similarities and the paucity of specific identification features. Using a combined morphologic and molecular approach has enabled differentiation of morphologically similar but genetically distinct species with identification of cryptic species (2). Sri Lanka has the highest number of human Dirofilaria spp. infections in Asia (6).
Figure 1
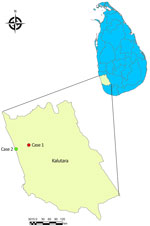
Figure 1. Locations of Dirofilaria asiatica microfilaremia cases in study of Dirofilaria infection and asymptomatic microfilaremia, Sri Lanka, 2025. Close-up view shows Kalutara district in western Sri Lanka....
Most Dirofilaria infections in humans are amicrofilaremic (1,5). The developmental cycle deviates as immature worms localize in aberrant hosts, triggering host inflammatory responses against Dirofilaria and Wolbachia (essential endosymbiont) antigens that arrest worm development or destroy them, resulting in inflammatory granulomas with indwelling immature worms (1). Thus, humans were regarded as dead-end hosts. However, occasional reports of microfilaremic infections have queried this theory (7,8). We report asymptomatic D. asiatica microfilaremia in 2 cases detected incidentally during night blood surveillance for lymphatic filariasis, in Kalutara district, in western Sri Lanka in 2025 (Figure 1).
Case 1 was in a 60-year-old mason who had a microfilaria count of 7 in a 60-µL night blood smear (NBS) in April 2025. The microfilaria was morphologically compatible with genus Dirofilaria. The patient was receiving treatment for diabetes mellitus and hypertension and had longstanding bilateral lower-limb swelling with no identifiable cause and a few palpable inguinal lymph nodes. Other physical examination results were unremarkable. Abdominal ultrasonography and ophthalmology screening results were unremarkable. After obtaining 5 mL of venous blood, we administered diethylcarbamazine (6 mg/kg/d for 12 d) and albendazole (400 mg). His microfilaremia was cleared at 5 weeks posttreatment.
Case 2 was in a 14-year-old boy who had a microfilaria count of 3/60 µL NBS in June 2025. The microfilaria was morphologically compatible with genus Dirofilaria. The patient had an occasional dry cough without diurnal variation. Hematology revealed eosinophilia of 568/μL (10.5%). Chest and abdominal imaging and echocardiography were unremarkable. He received doxycycline (100 mg 2×/d for 5 d) and albendazole (400 mg 2×/d for 5 d). Persistence of microfilaremia (1/60µL) at 1 month posttreatment necessitated a repeat course of treatment. His microfilaremia was cleared at 3 months posttreatment.
Figure 2
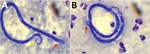
Figure 2. Microfilaria detected in Giemsa-stained thick blood smears from case-patients 1 (A) and 2 (B) in study of Dirofilaria infection and asymptomatic microfilaremia, Sri Lanka, 2025. Red arrows indicate...
Giemsa-stained NBSs from both case-patients at 1,000× magnification revealed microfilaria with morphology compatible with D. repens and D. asiatica worms (2). (Table; Figure 2). We performed molecular speciation to establish species identity. We extracted genomic DNA from venous blood of both patients using the QIAGEN Tissue Kit (QIAGEN, https://www.qiagen.com). We amplified mitochondrial cytochrome c oxidase subunit I (COI) gene using the primer pair COIfilF/COIfilR, designed from conserved nematode regions (9). We sequenced purified amplicons (QIAquick PCR Purification Kit; QIAGEN) bidirectionally by Sanger sequencing (SeqStudio Genetic Analyzer; Thermo Fisher Scientific, https://www.thermofisher.com) and deposited the resulting sequences in GenBank (accession nos. PZ359659 [AFC615] and PZ359660 [AFC621]). We edited chromatograms manually in BioEdit version 7.2.5 (https://www.updatestar.com) and queried against the National Center for Biotechnology Information nucleotide database using BLASTn (https://blast.ncbi.nlm.nih.gov/Blast.cgi) for homology assessment. We performed multiple sequence alignment using ClustalW in BioEdit. Both isolates were consistently identified as Dirofilaria asiatica; BLAST results showed near-complete query coverage (≈100%) and high percentage identity (>99%) to reference D. asiatica sequences, confirming species-level identification.
Figure 3
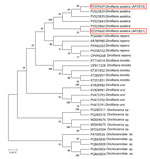
Figure 3. Maximum-likelihood phylogenetic tree generated in study of Dirofilaria asiatica infection and asymptomatic microfilaremia, Sri Lanka, 2025. Tree includes partial mitochondrial cox1 gene sequences from 2 ...
We constructed a maximum-likelihood phylogenetic tree in MEGA version 11 (10), using the best-fit substitution model selected by Bayesian Information Criterion (Figure 3). We assessed branch support using 1,000 bootstrap replicates and genetic distances estimated under the Kimura 2-parameter model. The resulting tree resolved 6 well-defined major clades, corresponding to D. asiatica, D. repens, D. immitis, D. ursi, Onchocerca sp., and Onchocercidae sp.; the deepest nodes separating the clades were supported at 10%–23%. Both study isolates, AFC615 and AFC621, clustered firmly within the D. asiatica clade alongside reference sequences also obtained from GenBank (accession nos. PV523839, PV523835, PV523843, and PV523842). Isolate AFC615 grouped closely with PV523839 and PV523835; bootstrap support was 99% at the terminal node and 97% and 91% at the supporting internal nodes. Isolate AFC621 formed a pair with reference sequence PV523842; the pair nested within the broader D. asiatica clade at 43% support. The clustering we observed was fully consistent with the BLASTn results, confirming both isolates as genuine D. asiatica.
Overall, the phylogenetic tree demonstrated clear separation of the 6 major clades (D. asiatica, D. repens, D. immitis, D. ursi, Onchocerca sp., and Onchocercidae sp.), with both study isolates aligning unambiguously within the D. asiatica lineage. The range of bootstrap support observed within this clade (22%–99%) reflects a degree of intraspecific genetic variation among D. asiatica sequences from different geographic sources, while clearly resolving both Sri Lanka isolates as D. asiatica (Figure 3).
Human Dirofilaria infections has been reported in Sri Lanka over many decades (6), although not specifically microfilaremia caused by D. asiatica filarial worms. Case-patient 1, who had underlying conditions, was probably immunodeficient to some extent, enabling the maturation of D. asiatica larvae into adults, whereas case-patient 2 may have had multiple exposure events.
A literature review revealed use of 3 treatment regimens with no preference of one over the other (11). The first 2 regimens were diethylcarbamazine/albendazole combination therapy or doxycycline/albendazole combination therapy targeting the endosymbiont Wolbachia. The third regimen was ivermectin (200 μg/kg/d for 4 d) and doxycycline (100 mg 2×/d for 7 d) (12). We used the diethylcarbamazine/albendazole and doxycycline/albendazole regimens because ivermectin was not registered for human use in Sri Lanka at the time of treatment. Although both treatment regimens achieved clearance of microfilaremia, the viability of adult worms remains uncertain; attempts to locate adult worms were unsuccessful. Thus, we deliberated recommendations for annual follow-up by blood screening for 5 years.
Our report establishes the presence of accidental D. asiatica infections among humans in Sri Lanka who were asymptomatic with microfilaremia. Further investigations will support the establishment of dirofilariasis as a zoonotic public health problem. We recommend routine administration of antifilarial drugs to dogs and cats, control of mosquitoes, and raising awareness of dirofilariasis.
Dr. Mataraarachchi was the acting consultant community physician attached to the Anti Filaria Campaign, Colombo, at the time of case detection. She is the regional epidemiologist, Matara, Regional Director of Health Services, Matara, Sri Lanka.
Acknowledgments
We gratefully acknowledge the technical support provided in obtaining the morphometry of microfilariae by Hemantha Sudusinghe. We also thank the medical registrars K.C.T. Wijayawardana and L.U.S. Seneviratna for assisting with medical screening of cases. We appreciate the valuable guidance provided by reviewers in the preparation of the manuscript.
Author contributions: D.M. initiated the study. D.M., I.A., M.V., P.S., and L.L. collected the data and samples for further studies. G.L. and N.P. were involved in case management. N.C. and S.R. guided the investigations. N.G. and T.S. performed molecular analysis. I.A., N.C., T.S., and S.R. drafted the report. All authors provided critical feedback and granted final approval.
References
- Simón F, Siles-Lucas M, Morchón R, González-Miguel J, Mellado I, Carretón E, et al. Human and animal dirofilariasis: the emergence of a zoonotic mosaic. Clin Microbiol Rev. 2012;25:507–44. DOIPubMedGoogle Scholar
- Colella V, Young ND, Manzanell R, Atapattu U, Sumanam SB, Huggins LG, et al. Dirofilaria asiatica sp. nov. (Spirurida: Onchocercidae)—defined using a combined morphological-molecular approach. Int J Parasitol. 2025;55:461–74. DOIPubMedGoogle Scholar
- Atapattu U, Koehler AV, Huggins LG, Wiethoelter A, Traub RJ, Colella V. Dogs are reservoir hosts of the zoonotic Dirofilaria sp. ‘hongkongensis’ and potentially of Brugia sp. Sri Lanka genotype in Sri Lanka. One Health. 2023;17:
100625 . DOIPubMedGoogle Scholar - Pampiglione S, Rivasi F. Human dirofilariasis due to Dirofilaria (Nochtiella) repens: an update of world literature from 1995 to 2000. Parassitologia. 2000;42:231–54.PubMedGoogle Scholar
- Magnis J, Lorentz S, Guardone L, Grimm F, Magi M, Naucke TJ, et al. Morphometric analyses of canine blood microfilariae isolated by the Knott’s test enables Dirofilaria immitis and D. repens species-specific and Acanthocheilonema (syn. Dipetalonema) genus-specific diagnosis. Parasit Vectors. 2013;6:48. DOIPubMedGoogle Scholar
- Balendran T, Yatawara L, Wickramasinghe S. Human dirofilariasis caused by Dirofilaria repens in Sri Lanka from 1962 to 2020. Acta Parasitol. 2022;67:628–39. DOIPubMedGoogle Scholar
- Poppert S, Hodapp M, Krueger A, Hegasy G, Niesen WD, Kern WV, et al. Dirofilaria repens infection and concomitant meningoencephalitis. Emerg Infect Dis. 2009;15:1844–6. DOIPubMedGoogle Scholar
- Frenzen FS, Loewe I, Müller G, Schoenlebe J, Tappe D, Teichmann D. Dirofilaria repens infection of the eye with concomitant microfilaremia in a traveller. J Travel Med. 2021;28:
taaa119 . DOIPubMedGoogle Scholar - Casiraghi M, Anderson TJ, Bandi C, Bazzocchi C, Genchi C. A phylogenetic analysis of filarial nematodes: comparison with the phylogeny of Wolbachia endosymbionts. Parasitology. 2001;122:93–103. DOIPubMedGoogle Scholar
- Tamura K, Stecher G, Kumar S. MEGA11: Molecular Evolutionary Genetics Analysis version 11. Mol Biol Evol. 2021;38:3022–7. DOIPubMedGoogle Scholar
- Valčiukaitė-Žilinskienė R, Zablockienė B, Zablockis R. Dirofilariasis presenting as pleural effusion: a rare case report with unusual manifestations and treatment modalities. BMC Pulm Med. 2024;24:340. DOIPubMedGoogle Scholar
- Biasizzo H, Šoba B, Ilovski F, Harlander M, Lukin M, Blatnik O, et al. Severe and rare case of human Dirofilaria repens infection with pleural and subcutaneous manifestations, Slovenia. Emerg Infect Dis. 2022;28:2504–7. DOIPubMedGoogle Scholar
Figures
Table
Suggested citation for this article: Mataraarachchi D, Abeysekara I, Narammalage H, Siriwardana T, Gunathilaka N, Vallipuranathan M, et al. Dirofilaria asiatica infection and asymptomatic microfilaremia, Sri Lanka, 2025. Emerg Infect Dis. 2026 Nov [date cited]. https://doi.org/10.3201/eid3211.260015
Original Publication Date: October 16, 2026
Table of Contents – Volume 32, Number 11—November 2026
| EID Search Options |
|---|
 Advanced Article Search – Search articles by author and/or keyword. |
 Articles by Country Search – Search articles by the topic country. |
 Article Type Search – Search articles by article type and issue. |
Please use the form below to submit correspondence to the authors or contact them at the following address:
Nilmini Chandrasena, Department of Parasitology, Faculty of Medicine, University of Kelaniya, Thalagolla Rd, Ragama, Sri Lanka
Top