Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 12—December 2026
Dispatch
Oropouche Fever Outbreak, Havana, Cuba, June–September 2024
 , Elba Cruz Rodríguez, Alexander González Díaz, Mayling Álvarez Vera, Niurka Molina Águila, Waldemar Baldoquin Rodríguez, Dayana Velázquez Rodríguez, María Eugenia Toledo Romani, José Raúl de Armas Farnández, Mayra García Carmenate, Vivian Kourí Cardellá, and María G. Guzmán
Suggested citation for this article
Abstract
Oropouche fever emerged nationwide in Cuba in 2024. We investigated the outbreak in Havana; of 549 suspected cases, 189 (34.4%) were confirmed. No cases were severe. Incidence was 8.9/100,000 population and was highest in adults 27–59 years of age (10.2/100,000 population). Three infants tested positive. Dengue cocirculation challenged surveillance.
Oropouche fever (OF) is an emerging arboviral disease caused by Oropouche virus (OROV), which is transmitted primarily by Culicoides paraensis biting midges (1). During 2024, OROV activity increased substantially across the Americas, including in countries in which no previous local transmission had been documented (2).
In Cuba, a passive arboviral surveillance system detects acute febrile illness through a network of polyclinics and hospitals (3). The country experiences frequent dengue outbreaks, which peak seasonally during May–November (4). Dengue IgM screening is performed in 30 regional laboratories. Confirmatory real-time PCR for OROV is centralized at the National Reference Laboratory of the Pedro Kourí Tropical Medicine Institute (NRL-IPK; Havana, Cuba) (3), where ongoing surveillance detects and monitors multiple arboviruses, including dengue, chikungunya, Zika, and Mayaro (3).
On May 27, 2024, the Ministry of Public Health reported an outbreak of OF in Cuba (5). The outbreak was detected in Santiago de Cuba and Cienfuegos Provinces, where acute febrile illness cases exceeded seasonal levels and results of dengue testing remained negative. The surveillance system generated an alert for a possible emerging pathogen (6). After OROV circulation was confirmed by real-time PCR at the NRL-IPK, testing was limited to a subset of suspected cases (rather than universal screening) because of reagent shortages and operational constraints. Within 3 months, the outbreak had spread nationwide, involving 109 municipalities across all 15 provinces (7). By the end of the year, a total of 24,259 suspected cases were identified through the national febrile surveillance system; 626 cases were confirmed as OF (8). In this article, we describe the epidemiologic behavior of the initial OF outbreak in Havana and examine its implications for surveillance in a dengue-endemic setting, given the city’s high population density, history of arboviral epidemics, and role as a national travel hub.
We conducted a descriptive outbreak investigation in Havana Province (population 2,122,057), which consists of 15 municipalities, including Cuba’s capital city, and accounts for ≈20% of the national population. The NRL-IPK Ethics Committee approved the investigation (approval no. CEI-IPK 54–24).
We analyzed data from febrile surveillance for June 1–September 7, 2024, a period that captures the onset and initial growth of the OF outbreak in Havana. We defined a suspected case as fever >38°C with headache and >1 additional symptom (myalgia, arthralgia, chills, low back pain, or photophobia), negative dengue IgM results, and residence in or travel to an area with confirmed OROV transmission or unusual febrile illness activity within the previous 2 weeks. A confirmed case required detectable OROV RNA by real-time PCR (9) (Appendix Table 1).
We collected demographic, clinical, and laboratory data from municipal databases and a standardized clinical–epidemiologic form developed by the NRL-IPK (Appendix Figure). We performed dengue IgM testing across the provincial laboratory network (3). OROV real-time PCR was performed at the NRL-IPK using a multiplex real-time protocol (10). We merged, verified, and cleaned data before analysis.
We calculated absolute and relative frequencies and incidence rates per 100,000 population using 2024 demographic projections from the National Bureau of Statistics and Information. Because selective sample referral precluded reliable municipality-specific incidence estimates, we present municipal-level data as frequencies only.
Figure
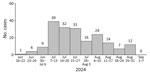
Figure. Epidemic curve of cases in Oropouche fever outbreak, Havana, Cuba, June 16–September 7, 2024 (N = 189). The first confirmed infection was identified on June 19.
During the study period, surveillance in Havana identified 21,744 suspected cases. Of the 549 samples tested by RT-PCR, 189 (34.4%) were positive for OROV. The earliest suspected case appeared on June 1, followed by the first confirmed OF case on June 19. Cases peaked at 39 during July 7–13 and stayed elevated over the next 2 weeks (32 cases and 31 cases), then declined to zero by early September (Figure). The overall incidence rate was 8.9/100,000 population.
OF cases appeared in 13 of 15 municipalities. Place of residence was known for 175 (92.6%) of 189 case-patients. La Lisa accounted for 94 (53.7%) of those cases. Cotorro reported no cases, and Regla submitted no samples for testing. Incidence peaked among adults 27–59 years of age (10.2/100,000 people) and was higher in female (9.4/100,000 population) than male (8.2/100,000 population) populations (Table). Three infants tested positive, including 2 neonates (8 days of age) who had no congenital anomalies.
Clinical data were available for 61/189 (32.3%) confirmed cases (Appendix Table 2). All patients had fever. The most frequent symptoms were headache (44/61 [72.1%]), malaise (36/61 [59.0%]), and myalgia (31/61 [50.8%]). Gastrointestinal symptoms consisted of anorexia (21/61 [34.4%]) and vomiting (20/61 [32.8%]). No cases were severe, and no deaths were reported.
During May–December 2024, Cuba reported 626 confirmed OF cases; 524 (83.7%) had occurred by September (8). The epidemic curve in Havana closely mirrored that national pattern: cases peaked during July 7–August 10 then declined in parallel with the rest of the country (8). That synchronized timing confirms that the local outbreak was an integral part of the nationwide epidemic.
The rapid spread of OROV across Cuba by mid-2024, months after its February introduction, suggests human mobility drove the outbreak. Previous estimates of 1.90 km/day dispersal and 70% long-distance viral spread align with this pattern, implicating commuting and interprovincial travel over vector dispersal alone (10).
C. paraensis midges were identified in Cuba during this outbreak (11). Cases clustered in western Havana municipalities (La Lisa, Playa, and Boyeros), areas historically prone to arboviral epidemics (11). That geographic concentration likely reflects local ecologic conditions that support vector establishment. Rising temperature, humidity, and rainfall during the study period (12) might have further amplified vector proliferation and transmission (13).
The first limitation of our study is that molecular testing was limited to a subset of suspected cases, which likely underestimated the true disease burden and introduced selection bias. Because sample referral was driven by operational logistics rather than random selection, we could not calculate reliable municipality-specific incidence rates or perform a comprehensive geographic risk assessment. In addition, mild or self-limiting infections in persons who did not seek medical care or infections that did not meet the criteria for testing were likely missed. The use of a dengue-adapted clinical–epidemiologic form might have missed OF-specific clinical features, and the mandatory negative dengue IgM result for case definition might have systematically excluded co-infections. Despite those constraints, our investigation provides useful evidence on urban OROV transmission and the resilience of integrated surveillance in resource-limited settings.
Detection of OROV in 3 infants, including 2 neonates, raises concerns about potential vertical transmission, as recently highlighted in Brazil (14). However, the absence of congenital anomalies or severe disease in our cases limits definitive conclusions about teratogenicity.
This investigation documents the rapid establishment of OROV transmission in an urban population and the national capacity to detect emerging pathogens in a dengue-endemic setting. Arboviral cocirculation strained both surveillance and clinical systems. First, event-based surveillance should complement formal reporting to absorb sudden surges of nonspecific febrile illness and rising healthcare demand. Second, clinicians faced overlapping symptoms and delayed laboratory confirmation, highlighting the need for faster testing and clearer clinical guidance. Third, our infant findings underscore the urgent need to integrate congenital and perinatal surveillance into existing maternal–child health programs. Strengthening laboratory capacity, expanding perinatal monitoring, and improving event-based detection are essential to mitigate future arboviral outbreaks.
Dr. Martínez-Rodríguez is a professor and researcher at the Department of Epidemiological Surveillance and Research at Pedro Kourí Tropical Medicine Institute. Her main research interests are epidemiological studies on tuberculosis, arboviruses, and pharmacoepidemiological studies.
Acknowledgments
We thank the Pan American Health Organization for its technical cooperation in the response to the Oropouche outbreak in Cuba. We are grateful to the investigators of the Department of Entomology and Arbovirus National Reference Laboratory of the Pedro Kourí Tropical Medicine Institute, particularly Ariamys Companioni, Gladys Gutiérrez, and Silvia Serrano. We also acknowledge the contributions of the infectologists from the Pedro Kourí Tropical Medicine Institute Hospital Center, especially Osvaldo Castro, for their insights into the clinical manifestations of Oropouche. Finally, we thank the specialists of the laboratory network for dengue virus IgM tests and the epidemiologists at the Provincial Center of Hygiene, Epidemiology, and Microbiology of Havana.
The Cuban Ministry of Public Health supported this study.
References
- Wesselmann KM, Postigo-Hidalgo I, Pezzi L, de Oliveira-Filho EF, Fischer C, de Lamballerie X, et al. Emergence of Oropouche fever in Latin America: a narrative review. Lancet Infect Dis. 2024;24:e439–52. DOIPubMedGoogle Scholar
- World Health Organization. Oropouche virus disease—region of the Americas [cited 2024 Aug 24]. https://www.who.int/emergencies/disease-outbreak-news/item/2024-DON530
- Guzmán MG, Vázquez S, Álvarez M, Pelegrino JL, Ruiz Amores D, Martínez PA, et al. Laboratory surveillance of dengue and other arboviruses in Cuba, 1970–2017 [in Spanish]. Rev Cuban Med Trop. 2019;71.
- Pérez M, Álvarez M, Perez L, Benitez AJ, Serrano S, Adelino TER, et al. Establishing a dengue genomic monitoring in Cuba: uncovering virus dynamics to enhance local response. IJID Reg. 2025;16:
100683 . DOIPubMedGoogle Scholar - World Health Organization. Oropouche virus disease—Cuba [cited 2024 Jun 20]. https://www.who.int/emergencies/disease-outbreak-news/item/2024-DON521
- Toledo ME, Monteagudo Diaz S, Montenegro Calderón T, Kreppel K, Van Damme E, Vanlerberghe V. Preparedness for emerging epidemic threats: detection of Oropouche circulation in Cuba. Lancet Infect Dis. 2024;24:
e484 . DOIPubMedGoogle Scholar - de Armas Fernández JR, García CEP, Herrera BA, García FD, Plaza IB, Carmenates IO, et al. Incidence of Guillain-Barré syndrome in Cuba before and during the Oropouche virus emergency, 2018-2024. J Neurol. 2025;272:164. DOIPubMedGoogle Scholar
- Organización Panamericana de la Salud. ARBO portal—Oropouche [cited 2025 August 20]. https://www.paho.org/es/arbo-portal/arbo-portal-oropouche
- Pan American Health Organization, World Health Organization. Epidemiological update: Oropouche in the Americas region [cited 2025 July 12]. https://www.paho.org/sites/default/files/2025-02/2025-feb-10-epi-update-oropoucheeng-final_0.pdf
- Gravier R, Perez MM, Álvarez M, Pérez L, Benítez AJ, Hernández D, et al. Spatiotemporal diffusion of the 2024 Oropouche outbreak in Cuba. Nat Med. 2026;32:2401–4. DOIPubMedGoogle Scholar
- Peláez Sánchez OR, Guzmán Tirado MG, Mas Bermejo P, Álvarez Vera M, Tejera Díaz JF, Peréz Cabrera S, et al. Contributions of clinical-seroepidemiological surveillance of dengue. 1997–2019 [in Spanish]. Anales de la ACC. 2023;13.
- Cedar Lake Ventures. Weather spark: historical weather data for 2024 at José Martí Airport, Cuba [cited 2025 May 13]. https://es.weatherspark.com/h/y/146734/2024/Datos-hist%C3%B3ricos-meteorol%C3%B3gicos-de-2024-en-el-Aeropuerto-Jos%C3%A9-Mart%C3%AD-Cuba#Figures-ColorTemperature
- Tegally H, Dellicour S, Poongavanan J, Mavian C, Dor G, Fonseca V, et al. Consortium CLIMADE. Dynamics and ecology of a multistage expansion of Oropouche virus in Brazil. Nat Ecol Evol. 2026;10:1114–26. DOIPubMedGoogle Scholar
- Pan American Health Organization, World Health Organization. Epidemiological alert Oropouche in the region of the Americas: vertical transmission event under investigation in Brazil—17 July 2024 [cited 2024 Aug 30]. https://www.paho.org/en/documents/epidemiological-alert-oropouche-region-americas-vertical-transmission-event-under
Figures
Table
Suggested citation for this article: Martínez-Rodríguez A, Cruz Rodríguez E, González Díaz A, Álvarez Vera M, Molina Águila N, Baldoquin Rodríguez W, et al. Oropouche fever outbreak, Havana, Cuba, June–September 2024. Emerg Infect Dis. 2026 Dec [date cited]. https://doi.org/10.3201/eid3212.251334
Original Publication Date: October 27, 2026
Table of Contents – Volume 32, Number 12—December 2026
| EID Search Options |
|---|
 Advanced Article Search – Search articles by author and/or keyword. |
 Articles by Country Search – Search articles by the topic country. |
 Article Type Search – Search articles by article type and issue. |
Please use the form below to submit correspondence to the authors or contact them at the following address:
Alina Martínez-Rodríguez, Tropical Medicine Institute “Pedro Kourí,” Autopista Novia del Mediodía, km. 6½ Arroyo Arenas, La Lisa, Havana, Cuba
Top