Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 10—October 2026
Dispatch
Chlamydia psittaci Meningitis, Chile, 2023
 , Cristian Rosas, Josefa Estefania Elmohrez, Jose Vicente Gonzalez, Teresa Tapia, and Juan Carlos Hormazabal
Suggested citation for this article
Abstract
We report a confirmed case of Chlamydia psittaci meningitis in Latin America, diagnosed in a 50-year-old farm worker from Chile. Diagnosis was established via cerebrospinal fluid quantitative real-time PCR and serology. The patient recovered after antimicrobial treatment. This case highlights the need to consider zoonotic pathogens in atypical meningitis.
Chlamydia psittaci is an obligate intracellular bacterium that causes psittacosis, a zoonotic infection typically transmitted through contact with infected birds, particularly Psittaciformes and poultry (1,2). In humans, psittacosis typically exhibits constitutional symptoms, including fever, chills, headache, and myalgia (3). Although widely associated with respiratory illness, the infection also can affect other organs, including the central nervous system (CNS), resulting in rare but serious manifestations, such as encephalitis and meningitis (4). We report a confirmed case of C. psittaci–associated meningitis in Latin America supported by molecular testing and serology.
A 50-year-old male farm worker from Puerto Octay, southern Chile, sought treatment at a rural health center on August 14, 2023, with fever >38°C, myalgia, chills, headache, and painful swallowing. Health center clinicians established a diagnosis of tonsillitis and treated the patient with intramuscular benzathine penicillin. Ten days later, the patient returned with persistent fever and headache and was referred to San José Hospital in Osorno with suspected meningitis. The patient worked as a tractor operator on a dairy farm, where he had occasional direct contact with cattle through participation in calving assistance and milking activities. He reported an increased number of bovine abortions on the farm during the months preceding illness onset. Although he denied direct contact with birds, he reported the presence of wild parrots and domestic chickens on the farm.
Figure
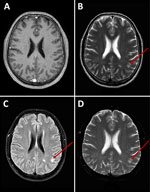
Figure. Axial brain magnetic resonance imaging of a patient with Chlamydia psittacimeningitis, Chile, 2023. A) T1-weighted image shows unremarkable appearance. B) T2-weighted image; C) fluid-attenuated inversion recovery image; and...
At admission, we noted an erythematous pharynx but found the patient to be alert and oriented. Neurologic examination revealed normal cranial nerves, preserved motor function and tone, and no signs of meningeal irritation. Laboratory results revealed leukocytosis (11,400/mm3, 65% neutrophils), elevated C-reactive protein of 16.8 mg/L (reference value <5 mg/L), and mildly elevated liver enzymes. Cerebrospinal fluid (CSF) was clear and colorless, with 1,033 leukocytes/mm3 (56% mononuclear, 44% polymorphonuclear), protein 1.21 g/L, and glucose 50.1 mg/dL. We performed Gram stain and multiplex meningitis/encephalitis PCR panel of the CSF that included human parechovirus, adenovirus, cytomegalovirus, human enterovirus, parvovirus B19, Epstein-Barr virus, herpes simplex virus (HSV) 1 and 2, human herpesvirus 6 and 7, mumps virus, varicella-zoster virus, Escherichia coli K1, Streptococcus pneumoniae, Hemophilus influenzae, Neisseria meningitidis, Streptococcus agalactiae, and Cryptococcus neoformans; all tests were negative. HIV serology, cryptococcal antigen testing, and Toxoplasma gondii PCR also produced negative results. Cranial computed tomography revealed no abnormalities; magnetic resonance imaging detected white matter hyperintensities in both hemispheres at T2W, FLAIR, and DWI sequences (Figure), which have been described in meningitis caused by other pathogens, such as cytomegalovirus and S. pneumoniae (5).
We treated the patient empirically with intravenous ceftriaxone, ampicillin, dexamethasone, and acyclovir. We discontinued acyclovir after CSF PCR testing for HSV-1 and HSV-2 yielded negative results. We tested CSF samples by quantitative real-time PCR for parvovirus B19, Brucella spp., Leptospira spp., and C. psittaci. We tested serum samples serologically for Coxiella burnetii, Brucella spp., Leptospira spp., and C. psittaci (Table). We performed all analyses at the national reference laboratory of the Institute of Public Health of Chile (Santiago, Chile).
Quantitative real-time PCR of CSF returned a positive result for C. psittaci, as did serologic testing by indirect immunofluorescence assay, with an IgG titer of 1:128 (positive cutoff >1:64) and an IgM titer of 1:10 (positive cutoff >1:10) (Table). The patient remained stable, without neurologic deficits. Follow-up brain magnetic resonance imaging on August 26, 2023, showed no pathologic findings. The patient completed a 7-day course of intravenous antibiotics followed by 7 days of oral levofloxacin. Outpatient follow-up confirmed full recovery.
Although human psittacosis has been previously reported in Chile, including a confirmed case in 1956, a family cluster in 1984, and a 15-case outbreak in 2021 in southern regions (6), none of those cases involved CNS manifestations. Our case expands the geographic recognition of C. psittaci meningitis and highlights the need to consider zoonotic pathogens in patients with atypical CNS infections in Latin America.
Meningitis caused by C. psittaci is exceedingly rare. To clarify the spectrum and rarity of CNS infection caused by C. psittaci, we conducted a PRISMA 2020 (7)–guided systematic review of published cases (Appendix). We identified only 6 previously published cases of molecularly confirmed C. psittaci CNS infection worldwide. Because we applied stringent eligibility criteria, requiring molecular confirmation in cerebrospinal fluid or CNS tissue, we excluded most historical reports that were diagnosed solely on the basis of serology or clinical findings (Appendix Table 1), leaving only a small number of well-characterized cases for comparison. According to those reports, clinical manifestations ranged from isolated meningitis to severe encephalitis with status epilepticus or cerebral vasculitis, whereas definitive diagnosis relied almost exclusively on molecular detection in cerebrospinal fluid (Appendix Table 2). Our findings emphasize both the exceptional rarity of confirmed CNS infection and the pivotal role of molecular diagnostics in recognizing this uncommon manifestation. We identified 6 reported cases diagnosed using molecular methods, 1 from the United States (8), 4 from China (9–12), and 1 from Austria (13), and compared those with our case from Chile (Appendix Table 3).
Diagnosis of psittacosis is challenging because C. psittaci cannot be detected by routine bacterial cultures. Serologic testing is more widely available but often requires paired samples, which might delay confirmation and can have cross-reactivity with other Chlamydia species. In contrast, PCR performed on specimens collected early in the course of illness provides the highest sensitivity and specificity (14,15). Metagenomic sequencing could be a complementary diagnostic tool for characterizing C. psittaci CNS infections, although its availability remains limited in many clinical settings. Diagnosis in this case was difficult because of nonspecific clinical findings and the absence of classic meningeal signs. Standard CSF panels and cultures were negative, highlighting the need for molecular testing and serologic investigation in patients with a compatible exposure history and negative routine workups.
Our case reinforces the need to consider zoonotic pathogens in rural and agricultural populations, particularly in Latin America, where psittacosis is underdiagnosed and potentially underreported. The favorable outcome also suggests that early empirical treatment with broad-spectrum antimicrobials, followed by targeted therapy, can be an effective approach. Doxycycline is the preferred antimicrobial agent for treating psittacosis (3,4), and 21-day duration is preferred in CNS involvement (9). Our case also highlights the diagnostic value of integrating epidemiologic history with molecular testing in evaluating atypical meningitis and emphasizes the importance of considering C. psittaci as a cause of CNS infection.
Dr. Pinos Garcia is an infectious diseases specialist at San Jose Hospital in Osorno, southern Chile. Her areas of interest include zoonoses, emerging infections, and One Health.
Acknowledgments
We thank the clinical and laboratory teams at San Jose Hospital in Osorno and the Institute of Public Health of Chile for their contributions.
This publication was approved by the ethics committee of the Los Ríos Health Service of Chile. Written informed consent for publication was obtained from the patient. All authors have read and provided consent to publish the current version of the manuscript.
References
- Beeckman DS, Vanrompay DC. Zoonotic Chlamydophila psittaci infections from a clinical perspective. Clin Microbiol Infect. 2009;15:11–7. DOIPubMedGoogle Scholar
- Ravichandran K, Anbazhagan S, Karthik K, Angappan M, Dhayananth B. A comprehensive review on avian chlamydiosis: a neglected zoonotic disease. Trop Anim Health Prod. 2021;53:414. DOIPubMedGoogle Scholar
- Ni Y, Zhong H, Gu Y, Liu L, Zhang Q, Wang L, et al. Clinical features, treatment, and outcome of psittacosis pneumonia: a multicenter study. Open Forum Infect Dis. 2023;10:
ofac518 . DOIPubMedGoogle Scholar - Centers for Disease Control and Prevention. Psittacosis: clinical guidance [cited 2025 Nov 15]. https://www.cdc.gov/pneumonia/atypical/psittacosis.html
- Perillo T, Capasso R, Pinto A. Neuroimaging of the most common meningitis and encephalitis of adults: a narrative review. Diagnostics (Basel). 2024;14:1064. DOIPubMedGoogle Scholar
- Ministerio de Salud de Chile. Psitacosis: epidemiological situation [in Spanish] [cited 2025 Nov 15]. https://epi.minsal.cl/psitacosis-situacion-epidemiologica
- Page MJ, McKenzie JE, Bossuyt PM, Boutron I, Hoffmann TC, Mulrow CD, et al. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ. 2021;372. DOIPubMedGoogle Scholar
- Davar K, Wilson MR, Miller S, Chiu CY, Vijayan T. A rare bird: diagnosis of psittacosis meningitis by clinical metagenomic next-generation sequencing. Open Forum Infect Dis. 2021;8:
ofab555 . DOIPubMedGoogle Scholar - Shi Y, Chen J, Shi X, Hu J, Li H, Li X, et al. A case of Chlamydia psittaci caused severe pneumonia and meningitis diagnosed by metagenome next-generation sequencing and clinical analysis: a case report and literature review. BMC Infect Dis. 2021;21:621. DOIPubMedGoogle Scholar
- Yin XW, Mao ZD, Zhang Q, Ou QX, Liu J, Shao Y, et al. Clinical metagenomic sequencing for rapid diagnosis of pneumonia and meningitis caused by Chlamydia psittaci. World J Clin Cases. 2021;9:7693–703. DOIPubMedGoogle Scholar
- Zhao C, Liu Y, Li J. Radiological features of encephalitis of chlamydia psittaci. Neurol India. 2026;74:378–9. DOIPubMedGoogle Scholar
- Zhang W, Zhang S, Huang X, Dai L, Gao Y, Cao H, et al. A case of Chlamydophila psittaci caused pneumonia and encephalitis diagnosed by metagenome next-generation sequencing and clinical analysis. Jundishapur J Microbiol. 2024;17:
e144399 . DOIGoogle Scholar - Walder G, Schönherr H, Hotzel H, Speth C, Oehme A, Dierich MP, et al. Presence of Chlamydophila psittaci DNA in the central nervous system of a patient with status epilepticus. Scand J Infect Dis. 2003;35:71–3. DOIPubMedGoogle Scholar
- Xu L, Zhang C, Shi W, Ma J, Wang G. Current status and challenges in the diagnosis and treatment of psittacosis. Infect Dis Immun. 2025;•••. DOIGoogle Scholar
- Nieuwenhuizen AA, Dijkstra F, Notermans DW, van der Hoek W. Laboratory methods for case finding in human psittacosis outbreaks: a systematic review. BMC Infect Dis. 2018;18:442. DOIPubMedGoogle Scholar
Figures
Table
Suggested citation for this article: Pinos Garcia YI, Rosas C, Elmohrez JE, Gonzalez JV, Tapia T, Hormazabal JC. Chlamydia psittaci meningitis, Chile, 2023. Emerg Infect Dis. 2026 Oct [date cited]. https://doi.org/10.3201/eid3210.251985
Original Publication Date: September 21, 2026
Table of Contents – Volume 32, Number 10—October 2026
| EID Search Options |
|---|
 Advanced Article Search – Search articles by author and/or keyword. |
 Articles by Country Search – Search articles by the topic country. |
 Article Type Search – Search articles by article type and issue. |
Please use the form below to submit correspondence to the authors or contact them at the following address:
Yazmin Pinos Garcia, Hospital Base San Jose Osorno - Internal Medicine - Infectious Diseases, Guillermo Bühler 1765, Osorno 5290000, Chile
Top