Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 10—October 2026
Research Letter
Haemophilus ducreyi Bacteria Causing Cutaneous Ulcer Outbreak in Children, Sierra Leone, December 2025
 , and Zhiqiang Mi
Suggested citation for this article
Abstract
We report a cutaneous ulcer outbreak in Sierra Leone in 2025 that predominantly affected ≈403 schoolchildren. The causative agent was confirmed as Haemophilus ducreyi, a bacterium traditionally associated with the sexually transmitted infection chancroid but more recently recognized as an emerging cause of lower limb cutaneous ulcers in tropical regions.
Nongenital cutaneous ulcers as a public health problem commonly affect children in many tropical regions, especially in West and Central Africa, the South Pacific, and South Asia (1). Yaws, which is caused by Treponema pallidum subspecies pertenue, has historically been considered the primary causative agent of such ulcers (2). In recent years, however, several studies have demonstrated that Haemophilus ducreyi is a leading bacterial cause of cutaneous ulcers (lower leg lesions in the absence of genital lesions) in yaws-endemic regions (3–5).
Figure 1
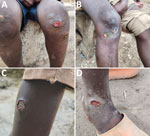
Figure 1. Irregular appearance of cutaneous ulcer lesions from patients in study of Haemophilus ducreyibacteria causing cutaneous ulcer outbreak in children, Sierra Leone, December 2025. A) Lesions over the knee....
Beginning on October 29, 2025, several clustered cases of lower limb cutaneous ulcers predominantly affecting schoolchildren in the Kayassie community, Safroko Limba Chiefdom, Bombali District, Sierra Leone, were reported to the National Public Health Agency of Sierra Leone. The infections were originally suspected to be Bacillus anthracis infection. Restriction of close student-to-student contact was advised for school management, while immediate laboratory testing for pathogen identification was launched. The outbreak showed sustained transmission: 266 cases by December 24, 2025; 386 cases by January 13, 2026; and 403 cases by February 10, 2026. Patients showed progressive skin ulcerations, sometimes associated with localized edema. The ulcers predominantly occurred on the lower limbs, where opportunistic skin injuries could easily develop, and commonly manifested as a localized lesion with an irregular border. The base of the ulcer was mostly composed of dry and crusted tissue without a purulent exudate (Figure 1). Recovery progressed steadily after case treatment and management (Appendix). Skin swab sample collection was conducted with consent from all participants or their parents or guardians, and the study was conducted using deidentified data derived from routine public health programmatic activities and interventions. The study was also reviewed and approved administratively by the National Public Health Agency of Sierra Leone.
B. anthracis infection was immediately excluded in the first 7 skin swab samples by using quantitative PCR targeting rpoB, pagA(pXO1), and capC(pXO2) (BioPerfectus Technologies, https://www.biosearchtech.com). Analysis of metagenomic sequence data produced from MinION (Oxford Nanopore Technologies, https://nanoporetech.com) (Appendix) revealed that H. ducreyi sequences were present in 4 of the 7 swab samples; no other relevant pathogens were identified (Appendix Figure 1). To confirm sequencing results, we performed real-time PCR according to a previous report (6). All of the first 7 samples tested positive for H. ducreyiThose preliminary results demonstrated that H. ducreyi was highly associated with this cutaneous ulcer outbreak.
As the outbreak progressed, another 149 swab samples were collected and shipped to the laboratory for PCR testing. Of the 156 total samples, 96 (61.5%) tested positive for H. ducreyi. No DNA evidence of T. pallidum subsp. pertenue, subsp. pallidum, or subsp. endemicum bacteria was detected by quantitative PCR in any of the 156 samples (7).
Figure 2
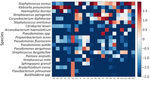
Figure 2. Heatmap of bacterial species investigated from study of Haemophilus ducreyi bacteria causing cutaneous ulcer outbreak in children, Sierra Leone, December 2025. Values are shown as log10(abundance...
To further determine the etiologic agent causing this outbreak, we sequenced genomic DNA from 22 swab samples (12 H. ducreyi–positive and 10 H. ducreyi–negative) on the DNBSEQ-G99 platform (MGI Tech, https://www.mgi-tech.com) (Appendix). Metagenomic analysis indicated no evidence of T. pallidum subsp. pertenue in the 22 samples, which is consistent with the PCR result. We identified no other etiologic pathogen associated with cutaneous ulcers in the 22 samples. The most abundant bacterial species were Staphylococcus aureus and Klebsiella pneumoniae (Figure 2).
To isolate H. ducreyi, we immediately inoculated 61 swab samples in the field onto Columbia blood agar base (Thermo Fisher Scientific, https://www.thermofisher.com), supplemented with 2.5% fresh yeast extract, 3 µg/mL of vancomycin, and 30% rabbit blood (8). After 96 hours of microaerophilic culture at 33°C, grayish-white pinpoint-sized colonies were picked up (9). After 3 consecutive subcultures, we confirmed PCR-positive colonies to be H. ducreyi (Appendix Figure 2). Among the 61 inoculated samples, H. ducreyi grew from 9 samples. Ambient transport temperature and lack of CO2 might have reduced isolation.
We sequenced the complete genomes of 9 H. ducreyi strains on an Illumina platform (https://www.illumina.com) (Appendix). Phylogenetic analysis demonstrated that the 9 isolates recovered in Sierra Leone formed a cluster with strains from Ghana and were distributed into 2 separate clades (Appendix Figure 3). We submitted short reads for 22 skin swab samples and 9 strains of H. ducreyi bacteria to the National Center for Biotechnology Information Sequence Read Archive (https://www.ncbi.nlm.nih.gov/sra; accession no. PRJNA1450830).
To try to determine a source for the outbreak, we tested 60 saline-soaked fly samples, 8 water samples from neighboring ponds, and tissue samples from 2 goats that died during the outbreak by quantitative PCR. No samples were positive for H. ducreyi.
This investigation confirmed that H. ducreyi was the causative bacterial agent of the cutaneous ulcer outbreak among children in Bombali District, Sierra Leone, in 2025. Sierra Leone is historically classified as a yaws-endemic country (10), and national eradication campaigns have been conducted in past decades. This outbreak, in essence, was a protracted, low-severity outbreak of cutaneous H. ducreyi infection, yielding no fatalities and leading to gradual resolution under enhanced surveillance and case management. However, the source of H. ducreyi in this outbreak remains unclear. Clinicians should be aware of the possibility of cutaneous H. ducreyi infection in yaws-endemic regions.
Dr. Zhang works at the Chinese Academy of Agricultural Sciences, the Changchun Veterinary Research Institute, Changchun, China. His primary research interest is detection, prevention, and control of bacterial pathogens causing zoonotic diseases.
Acknowledgment
We thank all study participants and their parents or legal guardians for their time, the field team from the National Public Health Emergency Operations Centre, the Bombali District Health Management Team, and the World Health Organization Country Office for Sierra Leone. We also thank Shiyang Cao for her constructive suggestions on the culture and isolation of H. ducreyi.
References
- Fegan D, Glennon MJ, Kool J, Taleo F. Tropical leg ulcers in children: more than yaws. Trop Doct. 2016;46:90–3. DOIPubMedGoogle Scholar
- Marks M, Mitjà O, Solomon AW, Asiedu KB, Mabey DC. Yaws. Br Med Bull. 2015;113:91–100. DOIPubMedGoogle Scholar
- Mitjà O, Lukehart SA, Pokowas G, Moses P, Kapa A, Godornes C, et al. Haemophilus ducreyi as a cause of skin ulcers in children from a yaws-endemic area of Papua New Guinea: a prospective cohort study. Lancet Glob Health. 2014;2:e235–41. DOIPubMedGoogle Scholar
- Ndzomo P, Tchatchouang S, Njih Tabah E, Njamnshi T, Tsanga MVN, Bondi JA, et al. Prevalence and risk factors associated with Haemophilus ducreyi cutaneous ulcers in Cameroon. PLoS Negl Trop Dis. 2023;17:
e0011553 . DOIPubMedGoogle Scholar - Simpson SV, Arima H, Behene E, Nundu SS, Hammond J, Atta-Owusu R, et al. Mapping the distribution of yaws and Haemophilus ducreyi in the western north region of Ghana. BMC Infect Dis. 2025;25:1763. DOIPubMedGoogle Scholar
- Glatz M, Juricevic N, Altwegg M, Bruisten S, Komericki P, Lautenschlager S, et al. A multicenter prospective trial to asses a new real-time polymerase chain reaction for detection of Treponema pallidum, herpes simplex-1/2 and Haemophilus ducreyi in genital, anal and oropharyngeal ulcers. Clin Microbiol Infect. 2014;20:O1020–7. DOIPubMedGoogle Scholar
- Chi KH, Danavall D, Taleo F, Pillay A, Ye T, Nachamkin E, et al. Molecular differentiation of Treponema pallidum subspecies in skin ulceration clinically suspected as yaws in Vanuatu using real-time multiplex PCR and serological methods. Am J Trop Med Hyg. 2015;92:134–8. DOIPubMedGoogle Scholar
- Sottnek FO, Biddle JW, Kraus SJ, Weaver RE, Stewart JA. Isolation and identification of Haemophilus ducreyi in a clinical study. J Clin Microbiol. 1980;12:170–4. DOIPubMedGoogle Scholar
- Alfa M. The laboratory diagnosis of Haemophilus ducreyi. Can J Infect Dis Med Microbiol. 2005;16:31–4. DOIPubMedGoogle Scholar
- Harding RD. A yaws campaign in Sierra Leone. Trans R Soc Trop Med Hyg. 1949;42:347–66. DOIPubMedGoogle Scholar
Figures
Suggested citation for this article: Zhang J, Lv P, Zhao T, Jiang H, Squire JS, Yonnie MS, et al. Haemophilus ducreyi bacteria causing cutaneous ulcer outbreak in children, Sierra Leone, December 2025. Emerg Infect Dis. 2026 Oct [date cited]. https://doi.org/10.3201/eid3210.260727
Original Publication Date: September 21, 2026
1These authors contributed equally to this article.
Table of Contents – Volume 32, Number 10—October 2026
| EID Search Options |
|---|
 Advanced Article Search – Search articles by author and/or keyword. |
 Articles by Country Search – Search articles by the topic country. |
 Article Type Search – Search articles by article type and issue. |
Please use the form below to submit correspondence to the authors or contact them at the following address:
Mohamed B. Jalloh, National Public Health Agency, 42A Main Motor Rd, Wilberforce Village, Freetown, Sierra Leone
Top