Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 11—November 2026
Dispatch
Serologic Assessment of Public Health Action Needed for Trachoma, Coastal Ecuador, 2021–2024

Figure 2
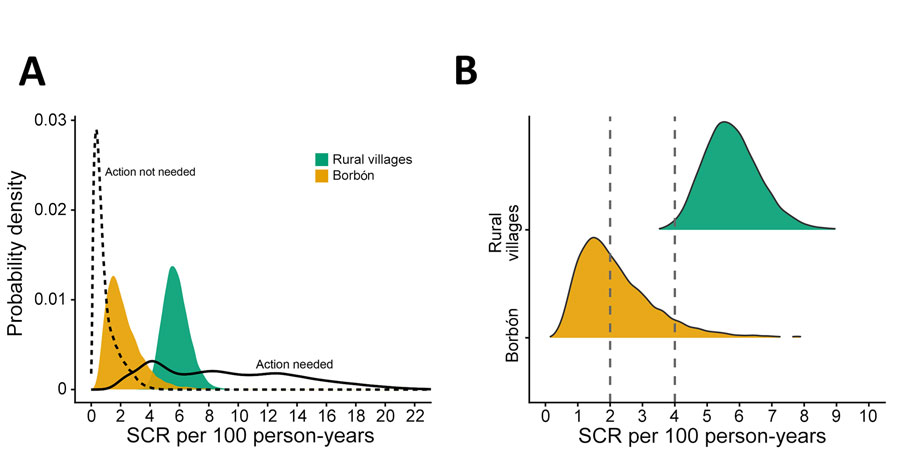
Figure 2. Model-based probability estimates of SCRs for IgGs against Chlamydia trachomatis plasma gene protein 3 in study of serologic assessment of public health action needed for trachoma, coastal Ecuador, 2021–2024. Estimates compared data from Esmeraldas Province in Ecuador and global trachoma serology distributions (5). A) Probability density of SCRs for Borbón (commercial center) and 9 rural villages estimated for children who were 1–5 years of age. We superimposed those data with pooled SCR distributions from populations classified as public health action not needed (dashed line) and public health action needed (solid line), according to public health responses for trachoma control in a global analysis across a range of disease endemicity (5). B) Ridgeline plot of SCR probability densities for Borbón and rural villages from panel A compared with illustrative thresholds of 2 and 4/100 person-years (vertical dashed lines). We identified SCR <2 as a region of >90% probability that public health action is not needed, whereas SCR >4 is a region of >90% probability that public health action is needed. Intermediate ranges of SCR that are >2 and <4 per 100 person-years could motivate additional testing (e.g., PCR testing for infection or consideration for further monitoring depending on programmatic context [5]). SCR, seroconversion rate.
References
- World Health Organization. Validation of elimination of trachoma as a public health problem. 2016 [cited 2026 Jun 3]. https://www.who.int/publications/i/item/who-htm-ntd-2016.8
- Solomon AW, Burton MJ, Gower EW, Harding-Esch EM, Oldenburg CE, Taylor HR, et al. Trachoma. Nat Rev Dis Primers. 2022;8:32. DOIPubMedGoogle Scholar
- Martin DL, Bid R, Sandi F, Goodhew EB, Massae PA, Lasway A, et al. Serology for trachoma surveillance after cessation of mass drug administration. PLoS Negl Trop Dis. 2015;9:
e0003555 . DOIPubMedGoogle Scholar - Tedijanto C, Solomon AW, Martin DL, Nash SD, Keenan JD, Lietman TM, et al. Monitoring transmission intensity of trachoma with serology. Nat Commun. 2023;14:3269. DOIPubMedGoogle Scholar
- Kamau E, Ante-Testard PA, Gwyn S, Blumberg S, Abdalla Z, Aiemjoy K, et al. Characterizing trachoma elimination using serology. Nat Commun. 2025;16:5545. DOIPubMedGoogle Scholar
- Pan American Health Organization. Initiative for the elimination of trachoma in the Americas [cited 2025 Dec 10]. https://www.paho.org/en/initiative-elimination-trachoma-americas
- Lee GO, Eisenberg JNS, Uruchima J, Vasco G, Smith SM, Van Engen A, et al. Gut microbiome, enteric infections and child growth across a rural–urban gradient: protocol for the ECoMiD prospective cohort study. BMJ Open. 2021;11:
e046241 . DOIPubMedGoogle Scholar - Andrade P, Sosa-Moreno A, Vivero S, Nipaz V, Lee GO, Cevallos W, et al. The impact of Zika emergence in remote communities in northwestern Ecuador. J Infect Dis. 2024;230:e1058–66. DOIPubMedGoogle Scholar
- Kamau E, Ante-Testard PA, Colado J, Nash SD, Martin DL, Arnold BF, et al. Data resource profile: global trachoma serology data repository. Int J Epidemiol. 2025;54:
dyaf183 . DOIPubMedGoogle Scholar - Nash SD, Astale T, Nute AW, Bethea D, Chernet A, Sata E, et al. Population-based prevalence of Chlamydia trachomatis infection and antibodies in four districts with varying levels of trachoma endemicity in Amhara, Ethiopia. Am J Trop Med Hyg. 2021;104:207–15. DOIPubMedGoogle Scholar
- Pan American Health Organization. Ecuador: partnership to eliminate trachoma as a public health problem [cited 2025 Dec 10]. https://www.paho.org/sites/default/files/2024-03/2024-cde-paho-canada-trachoma-public-health-ecuador.pdf
- World Health Organization. Design parameters for population-based trachoma prevalence surveys. 2018 [cited 2026 Jun 3]. https://www.who.int/publications/i/item/who-htm-ntd-pct-2018.07
- Harding-Esch EM, Burgert-Brucker CR, Jimenez C, Bakhtiari A, Willis R, Bejiga MD, et al. Tropical data: approach and methodology as applied to trachoma prevalence surveys. Ophthalmic Epidemiol. 2023;30:544–60. DOIPubMedGoogle Scholar
- Kamau E, Gass K, Harding-Esch E, Díaz MIS, Ante-Testard PA, Kello A, et al. Design considerations for incorporating serological monitoring into trachoma prevalence surveys. Am J Epidemiol. 2026;•••:
kwag245 ; Epub ahead of print. DOIPubMedGoogle Scholar