Disclaimer: Early release articles are not considered as final versions. Any changes will be reflected in the online version in the month the article is officially released.
Volume 32, Number 12—December 2026
Dispatch
Typhoid Fever–Like Manifestation of Scrub Typhus in Patient with Myelodysplastic Syndrome, China, 2025

Suggested citation for this article
Abstract
A 79-year-old man in China sought care for fever and syncope and was diagnosed with myelodysplastic syndrome. Bone marrow showed hemophagocytosis and macrophages resembling typhoid cells, but cultures excluded Salmonella infection. Targeted next-generation sequencing identified Orientia tsutsugamushi, and a concealed popliteal eschar was found. Scrub typhus can produce typhoid-like bone marrow morphology.
Scrub typhus remains a major cause of acute undifferentiated fever across the Asia-Pacific region. Approximately 1 million cases are reported annually (1). The diagnosis is straightforward when the classic triad of fever, rash, and eschar is present, but atypical manifestations, particularly in older or immunocompromised patients, can lead to delays in diagnosis (2).
Although the clinical overlap between typhoid fever and scrub typhus has long been recognized, the 2 diseases have not previously been linked at the level of bone marrow pathology. Typhoid cells (i.e., macrophages with distinctive eosinophilic granular cytoplasm) historically have been considered a hallmark of Salmonella bacterial infection in bone marrow (3,4). Whether other intracellular pathogens can produce morphologically identical cells has not been systematically examined. Furthermore, scrub typhus has undergone dramatic geographic expansion in China, where incidence increased >20-fold during 2006–2023, and the disease has spread from its historical focus in southern China to previously nonendemic northern provinces, including Shandong (3,5). We report a patient in whom bone marrow morphology strongly suggested typhoid fever but the actual pathogen proved to be O. tsutsugamushi bacteria. We obtained written informed consent from the patient for publication of this report and accompanying images.
A 79-year-old man, who was retired farmer from rural Shandong Province, came to the emergency department in October 2025 with 4 days of spiking fevers up to 39.5°C and rigors. Over the preceding month, he had experienced 4 syncopal episodes; each time he regained consciousness within minutes but had headache and dizziness afterward. He spent most of his days tending a backyard garden and had a long history of drinking ≈60 mL of liquor daily. He kept no animals and had not traveled recently.
On arrival, he looked pale. His temperature was 38.3°C, pulse 92, and blood pressure 136/78 mm Hg. The conjunctivae were blanched. Heart sounds were regular without murmurs, the lungs were clear, and the abdomen was soft with no organomegaly. Neurologic examination and electrocardiogram results were unremarkable. Cranial computed tomography showed only mild left anterior cerebral artery stenosis, insufficient to explain his syncopal episodes. Chest and abdominal computed tomography showed scattered lymphadenopathy in the anterior mediastinum and both inguinal regions (largest node 1.4 cm).
Laboratory studies revealed pancytopenia and multiorgan dysfunction: white cells 3,690 cells/μL (reference range 3,500–9,500 cells/μL); hemoglobin 8.5 g/dL (reference 13.0–17.5 g/dL); mean corpuscular volume 106.8 fL (reference 82–100 fL); platelets 84,000/µL (reference 125,000–350,000/μL); alanine aminotransferase 131 IU/L (reference 9–50 IU/L); aspartate aminotransferase 103 IU/L (reference 15–40 IU/L); lactate dehydrogenase 442 IU/L (reference 120–250 IU/L); creatinine 159 μmol/L (reference 57–111 μmol/L); activated partial thromboplastin time 49.8 seconds (reference 24.0–39.0 seconds); D-dimer 1.92 mg/L (reference 0.00–1.00 mg/L); and ferritin 757 ng/mL (reference 13–150 ng/mL) with low total iron binding capacity. Tests for brucellosis, HIV, bunyavirus, hepatitis, cytomegalovirus, and SARS-CoV-2 were all negative.
Bone marrow aspirate showed 23% ring sideroblasts, and next-generation sequencing (NGS) detected an SF3B1 mutation (c.1986C>A, variant allele frequency 50.63%) with a 45,X,-Y karyotype, establishing a diagnosis of myelodysplastic syndrome (MDS) SF3B1 (6). However, MDS alone could not account for the fevers, the syncopal episodes, or the lymphadenopathy.
Figure 1

Figure 1. Bone marrow morphology in samples from a 79-year-old man with scrub typhus and myelodysplastic syndrome, Shandong Province, China, 2025. A) High-power view showing a macrophage with abundant cytoplasm filled with...
Of particular note on the bone marrow aspirate were clusters of large macrophages whose cytoplasm was packed with fine eosinophilic granules (Figure 1). Those cells were morphologically indistinguishable from the typhoid cells long regarded as a hallmark of Salmonella enterica serovar Typhi bone marrow infection (3,4). Hemophagocytosis of red cells and platelets also was evident; the patient’s platelets dropped from 84,000/µL to 60,000/µL over just a few days.
The morphologic findings were strongly suggestive of enteric fever. However, the patient had no abdominal pain, no rose spots, and no diarrhea. Blood and bone marrow cultures grew nothing, and the Widal test was negative, leaving bone marrow morphology suggestive of typhoid fever but clinical manifestations that did not support this diagnosis.
Figure 2
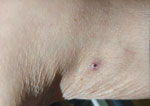
Figure 2. Eschar in the popliteal fossa of a 79-year-old man with scrub typhus and myelodysplastic syndrome, Shandong Province, China, 2025. A 5-mm eschar with central black necrosis and surrounding erythema was...
We sent the bone marrow aspirate for targeted NGS. The result, available on hospital day 6, was unexpected: Orientia tsutsugamushi was identified (2,7). (The O. tsutsugamushi targeted NGS sequence data have since been deposited in the National Center for Biotechnology Inofrmation Sequence Read Archive [BioProject accession no. PRJNA1470902; BioSample accession no. SAMN60430499]). A repeat physical examination of the patient found a 5-mm eschar with a dark necrotic center in the left popliteal fossa, an area easily overlooked was (Figure 2).The patient, when asked again, recalled no insect bite but confirmed he gardened barefoot and in shorts daily.
We administered intravenous doxycycline (100 mg 2/×d) (8). The patient’s fever broke within 48 hours. By day 7, his platelets had climbed to 152,000/µL, and transaminases had normalized (alanine aminotransferase 27 IU/L, aspartate aminotransferase 23 IU/L). At 3-week follow-up, the syncopal episodes had not recurred, and he began treatment for MDS.
Several aspects of this patient’s course deserve comment. First and foremost, a meticulous head-to-toe skin examination, with deliberate inspection of concealed areas including the axillae, groin, and popliteal fossae, might have revealed the eschar at admission and spared the patient a prolonged diagnostic workup. Shandong Province is a recognized endemic area for scrub typhus, and this simple clinical step remains the most accessible and cost-effective path to early diagnosis (4,7). The expanding geographic range of scrub typhus across China makes a thorough and systematic search for eschars all the more critical in the evaluation of febrile patients (3,5).
The bone marrow typhoid cells nearly led to a wrong diagnosis. Such distinctive macrophages have been considered relatively specific for enteric fever (3,4). That O. tsutsugamushi can produce morphologically identical cells expands the known spectrum of bone marrow pathology in scrub typhus. When such cells are encountered but microbiologic evidence of Salmonella infection is lacking, alternative intracellular infections, including scrub typhus, should be considered.
This patient exhibited features consistent with secondary hemophagocytic lymphohistiocytosis: spiking fevers, progressive pancytopenia, hyperferritinemia, elevated lactate dehydrogenase, and hemophagocytosis on bone marrow aspirate. In a systematic review by Naoi et al. (9), 30 patients with scrub typhus–associated hemophagocytic lymphohistiocytosis were analyzed; the overall mortality was 6.7%, and approximately half recovered with anti-rickettsial antibiotics alone. That pattern mirrors our patient’s course. The rapid normalization of platelet counts after doxycycline treatment (from 60,000/µL to 152,000/µL within 7 days) strongly suggests that the acute pancytopenia was driven primarily by scrub typhus–associated hemophagocytosis, rather than by MDS (10).
For diagnostic confirmation, specific PCR targeting of the 47 kDa gene of O. tsutsugamushi offers high sensitivity and is more widely available than sequencing-based methods (11). Where scrub typhus is clinically suspected, 47 kDa PCR should be the first-line molecular test. Targeted NGS retains value when the causative pathogen is not suspected, as in this patient.
Dr. Yu is a supervising technologist at Yuhuangding Hospital in Yantai, China. His primary research interests include microbial infection and immunity.
Acknowledgments
We thank the hospital staff for their support in sample collection and obtaining the patient’s history.
All authors contributed equally to this work. Y.L. managed the patient, conceived the report, and drafted the manuscript. W.W.H. and G.X.J. performed the bone marrow examination and provided pathologic images. G.Y.F. conducted the targeted NGS analysis and interpretation. All authors critically revised the manuscript and approved the final version.
References
- Devamani C, Alexander N, Schmidt WP, Stenos J, Cameron M, Abhilash KPP, et al. Incidence of scrub typhus in rural South India. N Engl J Med. 2025;392:2493–4. DOIPubMedGoogle Scholar
- Liu X, Zhang Y, Zhang J, Lou Z, Xia H, Lu Z. The early diagnosis of scrub typhus by metagenomic next-generation sequencing. Front Public Health. 2021;9:
755228 . DOIPubMedGoogle Scholar - Chen J, Chen H, Yang Y. Typhoidal cells: an uncommon diagnostic clue in Coxiella burnetii infection. Int J Lab Hematol. 2026;48:235–6. DOIPubMedGoogle Scholar
- Meiring JE, Khanam F, Basnyat B, Charles RC, Crump JA, Debellut F, et al. Typhoid fever. Nat Rev Dis Primers. 2023;9:71. DOIPubMedGoogle Scholar
- Sekeres MA, Taylor J. Diagnosis and treatment of myelodysplastic syndromes: a review. JAMA. 2022;328:872–80. DOIPubMedGoogle Scholar
- Malcovati L, Stevenson K, Papaemmanuil E, Neuberg D, Bejar R, Boultwood J, et al. SF3B1-mutant MDS as a distinct disease subtype: a proposal from the International Working Group for the Prognosis of MDS. Blood. 2020;136:157–70. DOIPubMedGoogle Scholar
- Xing F, Deng C, Huang J, Yuan Y, Luo Z, Lo SKF, et al. Usefulness of next-generation sequencing for laboratory diagnosis of rickettsiosis. PLoS Negl Trop Dis. 2024;18:
e0012546 . DOIPubMedGoogle Scholar - Varghese GM, Dayanand D, Gunasekaran K, Kundu D, Wyawahare M, Sharma N, et al.; INTREST Trial Investigators. Intravenous doxycycline, azithromycin, or both for severe scrub typhus. N Engl J Med. 2023;388:792–803. DOIPubMedGoogle Scholar
- Naoi T, Morita M, Kawakami T, Fujimoto S. Hemophagocytic lymphohistiocytosis associated with scrub typhus: systematic review and comparison between pediatric and adult cases. Trop Med Infect Dis. 2018;3:
E19 . DOIPubMedGoogle Scholar - Wu H, Xiong X, Zhu M, Zhuo K, Deng Y, Cheng D. Successful diagnosis and treatment of scrub typhus associated with haemophagocytic lymphohistiocytosis and multiple organ dysfunction syndrome: a case report and literature review. Heliyon. 2022;8:
e11356 . DOIPubMedGoogle Scholar - Jin YM, Liang DS, Huang AR, Zhou AH. Clinical characteristics and effective treatments of scrub typhus-associated hemophagocytic lymphohistiocytosis in children. J Adv Res. 2018;15:111–6. DOIPubMedGoogle Scholar
Figures
Suggested citation for this article: Li Y, Wang W, Gao X, Gu Y-f. Scrub typhus masquerading as typhoid fever in patient with myelodysplastic syndrome, China, 2025. Emerg Infect Dis. 2026 Dec [date cited]. https://doi.org/10.3201/eid3212.260686
Original Publication Date: October 23, 2026
Table of Contents – Volume 32, Number 12—December 2026
| EID Search Options |
|---|
 Advanced Article Search – Search articles by author and/or keyword. |
 Articles by Country Search – Search articles by the topic country. |
 Article Type Search – Search articles by article type and issue. |
Please use the form below to submit correspondence to the authors or contact them at the following address:
Yu-feng Gu, Clinical Laboratory Center, Yantai Yuhuangding Hospital, 20 Yuhuangding East Rd, Zhifu District, Yantai, Shandong 264000, China; email address:guyufeng87@hotmail.com
Top